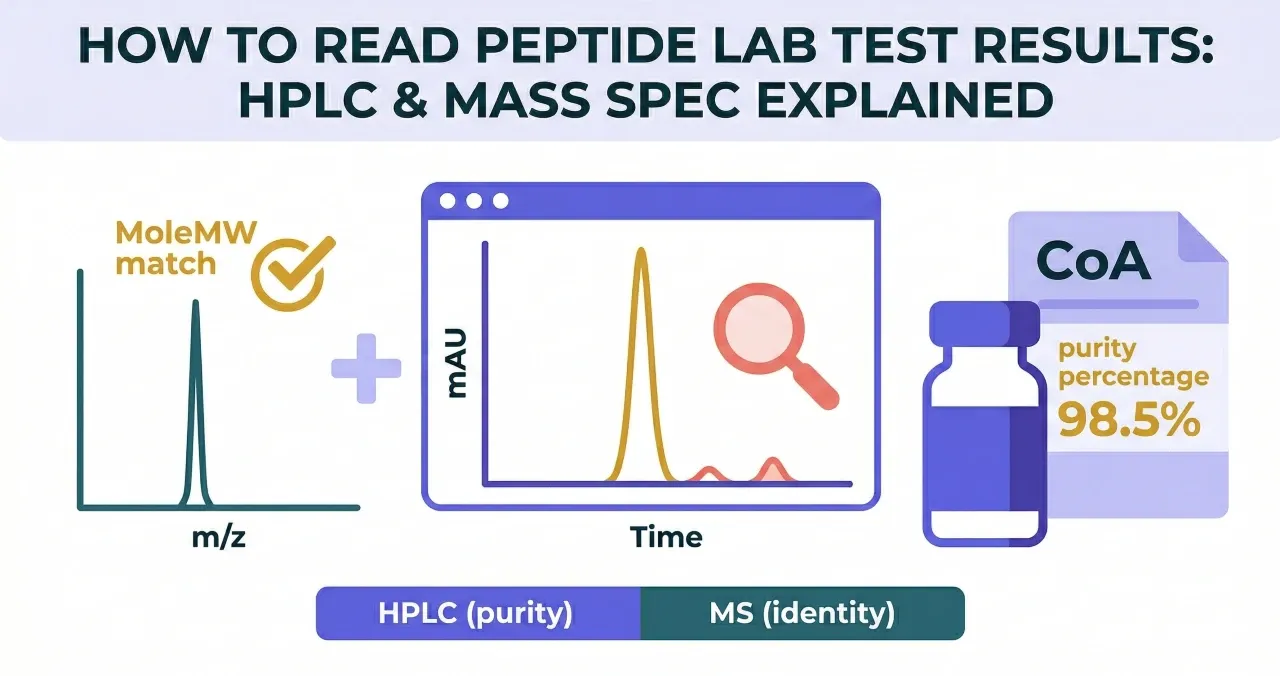
A peptide lab test result, the certificate of analysis, has four or five fields worth reading and one that everybody reads. The purity percentage is not the important one. Fill quantity is the most commonly documented real defect in this market, and purity testing does not measure it.
This page walks the document in the order the fields matter rather than the order they are printed. The methods behind two of those fields are explained in the HPLC article Why a Peptide Can Be 99 Percent Pure and Still Be Entirely the Wrong Molecule and in mass spectrometry for peptides; the forgery and formatting patterns belong to red flags in peptide certificates of analysis. Worked examples come from Peptigrity's own peptide lab tests and name the compound every time.
The short version
A certificate of analysis is a laboratory's report on one batch, and its purity percentage, the line everyone reads first, is the field least likely to be the problem.
Fill quantity is the most commonly documented real defect: in Peptigrity's COA benchmarks, 6.8% of shop-published certificates that measured the amount found less than 95% of the labelled amount, while 0.28% showed under 95% purity (verified October 2026).
A purity figure measures how uniform a sample is, not which molecule it is; identity needs a mass-spectrometry result, the test that weighs the molecule, read against a stated target mass.
A blank endotoxin field, the line for fever-causing bacterial residue, means nobody ran the test, not that the vial passed.
The reading order that follows the failure data is lot number, milligrams recovered, mass, salt form and endotoxin, with the purity percentage last.
What is actually on a peptide certificate of analysis?
Most certificates carry three fields and omit four. Purity, a mass and a batch reference are near-universal; salt form, quantitative content in milligrams, an endotoxin result and the instrument tier are frequently absent. That asymmetry is the whole problem, because purity, the field every certificate carries, answers a question that rarely fails in this market, and the four that vanish answer the ones that do. A gonadorelin vial labelled 5 mg tested at 2.12 mg, on a compound whose median purity is 99.76% (verified October 2026).
Field | Usually present? | What it answers | How often it is the actual failure |
|---|---|---|---|
Purity percentage | Yes | How homogeneous the sample was | Rarely — 0.28% of shop COAs fall below 95% (verified October 2026) |
Molecular weight / mass | Often | Which molecule, against a target | Sometimes, and decisively when it does |
Batch or lot number | Often | Whether the document describes your vial | Frequently, through mismatch |
Instrument tier | Rarely | Whether the mass can be defended | Decisive on sub-dalton pairs |
Salt form | Rarely | Which mass was weighed | Silently, up to 114 Da on MOTS-c |
Quantitative content (mg) | Rarely | Whether the vial matches the label | The most commonly documented real defect |
Endotoxin (LAL) | Rarely | Pyrogen load on an injectable | Unknown, because it is untested |
Read the right-hand column before anything else. The rest of this page works down it.
What is the purity percentage a percentage of?
Total detected peak area. An HPLC purity figure is the area under the main peak divided by the area under all detected peaks, expressed as a percentage, which makes it a measure of homogeneity and not of identity, potency or quantity. It is a percentage of one sample's chromatogram, not of the label. On Peptigrity's COA benchmarks, 0.28% of 11,767 shop-published certificates fall below 95% purity (verified October 2026), so a vendor promising "above 98%" is promising less than shops' own published certificates already show.
Two conditions have to hold before the number means anything. There must be a declared analyte for the percentage to be a percentage of, which excludes thymalin, Cortexin and Retinalamin — undefined animal-tissue extracts with no sequence, molecular weight or CAS number, where a purity figure is a category error rather than a weak result. And the figure has to be read against that compound's own observed baseline rather than a generic threshold: GHK-Cu's median across 621 shop-published certificates is 99.76%, and nine in ten sit at or above 99.28% (verified October 2026), so a 98% house standard sits below at least nine in ten of the results on record.
The second condition is the one vendors exploit, and it is easy to check. Read the compound's live range on the COA benchmarks page, What peptide COAs show — and what they leave out, rather than a number quoted in prose, and treat an unattributed certificate as a claim rather than a measurement. Benchmarks are handled in peptide purity standards, and the laboratories themselves in third-party peptide testing labs.
What does the retention time field tell you?
When the main peak came off the column, in minutes, and nothing else on its own. Retention time is a method-dependent number: it depends on the column chemistry, the solvent gradient, the flow rate and the instrument, so two laboratories testing the same vial will print different figures and neither is wrong. It becomes a check only when a reference standard is run on the same method in the same sequence and the two times are compared.
That comparison is what a certificate almost never shows you. A retention time quoted without the method that produced it — column, gradient, flow rate — is not something anyone can repeat or falsify, which makes it documentation rather than evidence.
It also fails exactly where a buyer most needs it. Retention time cannot separate compounds that co-elute, and the market's hardest identity pairs are the ones that do: PT-141 and melanotan II share a backbone and differ by about one dalton at the C-terminus, an all-D sequence and its all-L mirror image co-elute on the achiral reversed-phase columns used for purity testing, and oxytocin and vasopressin co-elute closely at a 77-dalton separation. Where the retention time would be most useful, chromatography has already given up.
Is the mass on the certificate nominal or high-resolution?
Ask, because the answer decides what the number is worth. A nominal-mass result reports a rounded figure and settles gaps of tens or hundreds of daltons — tesamorelin at 5,136 Da sits 1,778 above sermorelin, kisspeptin-54 at 5,857.5 sits 4,555 above kisspeptin-10 — and it cannot defend a sub-dalton discrimination. PT-141 at 1,025.2 and melanotan II at 1,024.18 are about 1.0 dalton apart on 1,025, under 0.1%, and a certificate printing "1,025" has not answered the question.
Three follow-up questions turn a mass field into an identity result. What target mass was the measurement read against, because IGF-1 LR3's quoted 9,111 daltons returns zero hits in a full-text Europe PMC search for the extension sequence it rests on, and a result of "approximately 9,000 Da" confirms nothing without a reference. Was an elemental composition reported, because sermorelin at 3,357.9 and Mod GRF (1-29) at 3,367.9 are 10 daltons apart and the substitution removes the molecule's only sulfur, turning an ambiguous margin into C₁₄₉H₂₄₆N₄₄O₄₂S against C₁₅₂H₂₅₂N₄₄O₄₂. And were terminal modifications confirmed, because gonadorelin's pyroglutamate and glycinamide are both required for receptor binding at 1,182.29 Da, and a des-acetyl thymosin alpha-1 is 42 daltons lighter than the 3,108.3 Da real thing.
Question to ask | Why it changes the answer | Named case |
|---|---|---|
Nominal or high-resolution? | Sub-dalton pairs need decimals | 1,025.2 vs 1,024.18 |
Read against what target? | No reference, no identification | IGF-1 LR3, 9,111 Da unsourceable |
Elemental composition reported? | Converts 10 Da into a binary | Sulfur present or absent on sermorelin |
Terminal modifications intact? | They carry the activity | 42 Da acetyl; pyroglutamate and glycinamide |
There are also masses no instrument will settle. D and L amino acids are isobaric, so FOXO4-DRI's all-D design and SS-31's D-arginine are invisible; misfolded protein has the same mass as correctly folded protein, so IGF-1 disulfide pairing is untestable; and a PEGylated product returns an envelope rather than a peak. When the mass field is blank on those compounds, the honest reading is that nothing was available to print.
Which salt form was weighed, and what is net peptide content?
Two separate lines, both usually missing, both moving real milligrams. Salt form changes the mass on the scale without changing the peptide: MOTS-c is supplied at 2,174.6 free base, 2,234.64 acetate and 2,288.6 TFA salt, a 114-dalton spread and about 5% of what is being weighed, so a vial labelled 10 mg of TFA salt contains roughly 9.5 mg of peptide. Net peptide content is the separate figure that strips salts and residual water out of the weight.
That is chemistry rather than a defect. It becomes a defect only when the certificate fails to state which form was weighed, because the dose calculation then uses a different quantity than the balance did. Semax makes the same point in a different way: Sigma-Aldrich supplies it as a TFA salt while quoting molecular weight on a free-base basis, and an acetate-salt record exists at 874.0 g/mol against the 813.93 free base.
Line | What it establishes | How it is reported | Red flag |
|---|---|---|---|
Salt form | Which of the possible masses was weighed | "Free base", "acetate" or "TFA" named | Not stated — a silent 5% dose error on MOTS-c |
Net peptide content | Peptide versus salts and water | Net content or amino acid analysis | Purity quoted as though it were quantity |
Quantitative content (mg) | Whether the vial matches the label | mg recovered, reported separately | Absent from the document entirely |
The bottom two rows are commonly confused and they are not the same measurement. Net peptide content answers how much of the powder is peptide; quantitative content answers how much peptide is in the vial against what the label promised. Both are covered in Peptide Net Content and TFA vs Acetate vs Amidate.
Does the vial contain what the label says?
Quantitative content fails more often than any other recorded field, and purity testing does not measure it. Across Peptigrity's dataset (verified October 2026) the largest documented anomalies are quantity anomalies, not purity anomalies: a cagrilintide vial labelled 10 mg assayed at 19.4 mg, a gonadorelin vial labelled 5 mg assayed at 2.12 mg, and a mazdutide vial labelled 20 mg assayed at 15.18 mg while testing 99.80% pure. A high purity percentage and a badly wrong fill are entirely compatible, and they appear on the same document.
Compound | Label | Assayed | Deviation | Context |
|---|---|---|---|---|
Cagrilintide | 10 mg | 19.4 mg | +94% | June 2026, ILS Laboratories, at 99.57% purity; cagrilintide results run from 20% to 194% of label across 258 single-vial certificates |
IGF-1 LR3 | — | — | median +10% | One June 2026 sample 72% over label, and 46 of 139 measured vials more than 20% over, on a compound whose signature adverse effect is hypoglycaemia |
Gonadorelin | 5 mg | 2.12 mg | −57.6% | April 2025, Vanguard Laboratory; median purity 99.76% across 13 tests |
Follistatin | 1 mg | 0.6 mg | −40% | May 2026; one of only 7 tests on the compound |
Survodutide | — | — | −13% to +46.7% | A sixty-point spread on a drug titrated toward 6.0 mg |
Tirzepatide | — | — | median +9% | Titrated in 2.5 mg steps; 11% of 1,033 shop COAs more than 20% over label and 0.7% more than 10% under; median purity 99.81% |
Mazdutide | 20 mg | 15.18 mg | −24.1% | April 2026, while testing 99.80% pure |
Sermorelin | 10 mg | 12.88 mg | +28.8% | Fill accuracy uncontrolled in both directions |
Selank | 10 mg | 12.86 mg | +28.6% | June 2026; median purity 99.73% across 322 COAs; one 5 mg vial read 11.43 mg |
PT-141 | 30 mg | 34.9 mg | +16.3% | A second sample read 11.63 mg on a 10 mg label |
Kisspeptin | 10 mg | 11.41 mg | +14.1% | Median purity 99.60% across 172 COAs; one 10 mg vial read 30.62 mg |
PEG-MGF | 5 mg | 6.35 mg | — | March 2026 |
Read overages as filling inconsistencies rather than generosity, with one caveat that How Peptigrity actually works spells out: some laboratories weigh the gross powder in the vial, salts and moisture included, against a label that states net peptide, so a reading well over 100% can be a gross-mass figure rather than a real overfill, and certificates often do not say which basis they used. Where an overage is real, a fill line running 28.8% over is a fill line nobody is measuring, and the same absence of control produces the shortfalls in the same table.
Where the compound is titrated, a quantity error is a dosing error with a direct mechanism. The Zepbound label, ZEPBOUND® (tirzepatide) Injection, for subcutaneous use (revised August 2026), escalates the weekly dose in 2.5 mg steps, at least 4 weeks apart. The SYNCHRONIZE-1 paper Survodutide Once Weekly for the Treatment of Adults with Obesity (le Roux et al., 2026) titrated survodutide up to 3.6 or 6.0 mg weekly in 725 adults with obesity. The REDEFINE 1 paper Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (Garvey et al., 2025) gave cagrilintide at 2.4 mg weekly, in combination with semaglutide, in a 68-week trial of 3,417 adults. On a hypoglycaemic agent like IGF-1 LR3, a 72% overage has an obvious route to harm.
Stop and seek care: swelling of the face or throat, difficulty breathing or hives after an injection are signs of a serious allergic reaction; spreading redness, warmth or pus at an injection site with fever is an infection; severe or persistent abdominal pain with vomiting on a GLP-1 drug can be pancreatitis; confusion, sweating or shaking on an IGF-1 or insulin-adjacent compound can be hypoglycaemia. Call your local emergency number (911 in the US, 112 in the EU, 999 in the UK, 000 in Australia) or go to an emergency department, and bring the vial and its label. Research-use vials are not approved products in any jurisdiction, even where a prescription product of the same molecule exists; no article on this site replaces a clinician who knows your history.
The practical instruction is a single line on the document: quantitative content in milligrams, on your batch, reported separately from purity. If it is absent, the vial's most likely defect has not been tested for. Volume arithmetic afterwards belongs to the tirzepatide calculator and the reconstitution calculator.
Where is the endotoxin result, and what does its absence mean?
Almost always absent, and absence means untested rather than clean. Endotoxin is measured by the LAL assay and reported in endotoxin units; on this platform it is missing far more often than it is present, with only 8 of 46 thymalin tests carrying a result, most survodutide tests reporting none, one of seven follistatin tests reporting one, and endotoxin data largely absent across PT-141, melanotan II and sermorelin listings (verified October 2026).
Where Semax results exist, on 65 of the 300 single-vial certificates (verified October 2026), the compound page prints only "Pass" or "Reported", and the certificates behind those marks mix laboratory limits with measurements: a limit of 0.05 EU/mL on one, 0.5 EU/mL on another, a measured 0.096 EU/mL on a third. A pass against one laboratory's limit is not the same result as a pass against another's.
A blank endotoxin field is not a pass. It is a field nobody filled in, and it matters most on exactly the products where it is least often reported: material derived from animal tissue, where pyrogen contamination is the realistic failure mode rather than a theoretical one, and compounds for which FDA, on its page Certain Bulk Drug Substances for Use in Compounding that May Present Significant Safety Risks (current as of April 2026), has named immunogenicity and peptide-related impurities as its stated concern.
For thymalin and its class the ordering inverts completely. Endotoxin and sterility testing carry more weight than purity there, because purity testing cannot perform its usual identity function against an undeclared analyte. Ask a vendor for an LAL result on the specific batch before asking about purity, as Endotoxin Testing for Peptides and Peptide Sterility Testing Explained set out.
Does the certificate describe your batch, and when was it run?
Check the lot number against the vial before reading anything else. Substitution and fill risk are per-batch rather than per-vendor, so a specimen certificate from an earlier lot describes a different vial made on a different day, and it is the single most common way a technically genuine document becomes useless. The test date matters for the same reason: gonadorelin's 13 tests (verified October 2026) span April 2025 to June 2026, and a result from the start of that window says nothing about material shipped at the end of it.
Three questions settle provenance. Is the laboratory named, because an unattributed certificate is a claim rather than a measurement — the laboratories behind this platform's data include Freedom Diagnostics, Kovera, ILS, Janoshik, Vanguard, Bioviridian, MZ Biolabs, Ethos Analytics, Chromate, Accumark and Liquilabs, and the directory of peptide testing labs lists each one's test record and stated methods. Is it third-party, because a vendor's own in-house document is not independent testing. And does the lot on the document match the lot on the vial in your hand.
Independent submission is the way past all three, and it is available: how to get your peptides independently tested covers the process, how to evaluate a peptide testing lab covers choosing one, and Janoshik Lab Review covers the laboratory with the second-largest test record on this platform (verified October 2026).
What does a good certificate look like beside a bad one?
A good certificate names the laboratory, matches your lot, dates the test, states the instrument tier, prints a target mass beside a measured one, names the salt form, reports milligrams recovered as a separate line from purity, and carries an LAL figure. A bad one prints a purity percentage, a rounded mass and a logo. The difference is not presentation quality — several of the worst documents in this market are the most professionally typeset.
Field | A certificate worth acting on | A certificate that is decoration |
|---|---|---|
Laboratory | Named third-party lab | Unattributed, or the vendor's own |
Batch | Lot matches your vial | Specimen certificate from an earlier lot |
Date | Recent, and printed | Absent, or years old |
Purity | Percentage plus the method | A percentage alone |
Mass | Measured against a stated target, tier named | A rounded number with no target |
Salt form | Named — free base, acetate, TFA | Absent |
Quantity | mg recovered, separate line | Absent, or purity offered instead |
Endotoxin | LAL result in EU | Field blank |
Common reading | What the evidence shows | Verdict |
|---|---|---|
"99% pure means I got the right compound" | Purity is a proportion, not a species | False |
"99% pure means the vial holds 10 mg" | Cagrilintide: 19.4 mg on a 10 mg label | False |
"A high percentage means it has not degraded" | Uniform degradation gives one clean peak | False |
"The mass field confirms identity" | True only if the tier and target are stated | Conditionally true |
"A blank endotoxin field means no endotoxin" | It means untested | False |
"A purity figure on thymalin means what it means elsewhere" | No declared analyte exists | Category error |
"The certificate in the listing describes my vial" | Risk is per-batch | Only if the lot matches |
"Third-party testing is standard in this market" | Quantity, salt form and endotoxin are usually absent | Overstated |
What do the lab tests on Peptigrity show about which field fails?
The lab tests on Peptigrity show that purity is largely solved and quantity is not, and they say nothing about identity, because mass-spectrometry results are not recorded. Tirzepatide's 1,033 shop-published certificates carry a median purity of 99.81% (verified October 2026), yet the middle 80% of measured amounts runs from 99% to 120% of the label, with 11% more than 20% over and 0.7% more than 10% under, on a drug titrated in 2.5 mg steps. The percentage is excellent. The milligrams are not.
That pattern repeats across the platform: in Peptigrity's COA benchmarks, 6.8% of 11,655 shop-published certificates with a measured amount came in below 95% of the labelled amount, against 0.28% of 11,767 below 95% purity (verified October 2026). Those certificates are a best case: 11,790 of the 11,793 were published by the shop selling the vial, and shops choose which results to make public. The platform tracks 789 shops, 13,520 third-party lab tests, 118 peptides and 976 community reviews (verified October 2026), with trust scores weighted 50% community reviews and 50% independently verified lab purity and no payment influencing the ranking. We publish the purity averages because they are what the laboratories reported, and we would not want anyone reading them as a statement about fill accuracy, identity or sterility.
Tirzepatide is in stock at 36 shops, with a lowest tracked price of $1.00/mg on a 140 mg vial and a median of $3.85/mg across 140 comparable offers in vials from 5 mg to 140 mg (verified 23 October 2026); band medians run $8.00, $5.00 and $3.50 per mg for small, mid and bulk vials. Those figures, read on the tirzepatide price comparison, exclude shipping, taxes and customs, coupon codes, bulk tiers, multi-vial kits and account-gated pricing. Compare within a single vial-size band, because fixed per-vial costs push the per-milligram figure down as fill size rises. Shop-level detail, for the shops that have chosen to appear, sits on the Tirzepatide compound page.
What trial would settle which certificate fields predict a good vial?
No study has followed certificates through to independently assayed vials and reported which fields predicted a correct product. This page ranks fields by how often they fail in our own dataset, which is a real observation and a weaker thing than a prospective test — the anomalies are documented, the predictive value of each field is not. We would rather state that than present a reading order as a validated instrument.
Element | What it would need |
|---|---|
Design | Prospective, blinded: certificates collected at purchase, vials independently assayed on arrival |
Exposure | Presence or absence of each field — instrument tier, target mass, salt form, mg recovered, LAL, lot match |
Primary endpoint | Proportion of vials within ±10% of label |
Secondary endpoints | Correct identity by high-resolution MS; endotoxin within limit; purity against the compound's own baseline |
Sample frame | Across compounds with known failure modes — cagrilintide, gonadorelin, IGF-1 LR3, tirzepatide |
What exists today | 13,520 published tests (verified October 2026) with documented anomalies, and no prospective certificate-to-vial linkage |
In what order should you read a certificate?
Read the lot number, then the quantity line, then the mass field with its tier and target, then the salt form, then the endotoxin result, and read the purity percentage last. That order inverts how certificates are laid out and how vendors present them, and it follows the failure frequency in the 11,793 certificates behind Peptigrity's COA benchmarks (verified October 2026) rather than the visual hierarchy of the document.
The single sentence worth carrying away is that purity is the field most likely to be present and least likely to be the problem. A vial can be 99.80% pure and 24.1% short, 99.57% pure and 94% over, or 99.82% pure, the median on PT-141 certificates (verified October 2026), while holding melanotan II — and all three would look reassuring on a certificate at a glance.
Browse the weight loss and metabolic peptides category, or all 118 compound pages under research peptides and their lab data (verified October 2026). Compare shops on their third-party lab tests and community reviews in the peptide suppliers directory, and work the full sequence in how to verify peptide quality before you buy.
Frequently Asked Questions
Which field on a certificate of analysis matters most?
Quantitative content in milligrams, on your batch, reported separately from purity. Fill quantity is the most commonly documented real defect in this market — a cagrilintide vial labelled 10 mg assayed at 19.4 mg, a gonadorelin vial labelled 5 mg assayed at 2.12 mg — and purity testing does not measure it. If that line is absent, the likeliest defect has not been tested for.
Can a vial be 99% pure and still be wrong?
Yes, in three separate ways. It can be the wrong molecule, because purity measures homogeneity rather than identity. It can hold the wrong amount, as a mazdutide sample did at 15.18 mg against a 20 mg label while testing 99.80% pure. And it can be degraded, because a vial in which every molecule oxidised the same way still returns one clean peak.
What does the retention time on a chromatogram tell me?
Only when the peak eluted, on that laboratory's column, gradient and instrument. Two labs testing the same vial print different figures and neither is wrong. It becomes a check only against a reference standard run on the same method, and it cannot separate compounds that co-elute, which includes the market's hardest pairs.
How do I know if the mass on my certificate is good enough?
Ask whether it was nominal or high-resolution, and what target it was read against. Nominal resolution settles the 1,778-dalton gap between tesamorelin and sermorelin and fails on the roughly one-dalton gap between bremelanotide and melanotan II. Without a stated target mass, as with IGF-1 LR3, the reading confirms nothing at all.
Does a blank endotoxin field mean the product is clean?
No, it means nobody ran the assay. Endotoxin reporting is sparse across this market — only 8 of 46 thymalin tests carry a result (verified October 2026), and it is largely absent from PT-141, melanotan II, sermorelin and survodutide listings. For injectable material derived from animal tissue, an LAL result on the specific batch is worth more than a purity percentage.
Should I trust a certificate the vendor supplies?
Only after three checks: the laboratory is named, it is genuinely third-party rather than in-house, and the lot number matches the vial in your hand. A specimen certificate from an earlier batch is a document about a different vial. Independent submission removes the question, and how to test your peptides documents the process.
This article is for educational and informational purposes only and does not constitute medical advice. Peptides discussed may be investigational compounds not approved by the FDA (or equivalent regulators in your jurisdiction) for human use; research peptides are sold for laboratory use and are not manufactured, tested or labelled to pharmaceutical standards. Peptigrity does not recommend doses: every dose figure above is an approved-label value, a published-trial value or a community report, and is labelled as such — a community report is not a recommendation. Self-injection carries risks of infection, allergic reaction and dosing error; signs of a serious allergic reaction, an injection-site infection with fever, severe abdominal pain, or confusion and sweating on an IGF-1 or insulin-adjacent compound are medical emergencies — call your local emergency number. Always consult a qualified healthcare provider before using any peptide or research compound. Peptigrity is an independent review platform and does not sell, endorse, or recommend specific products or vendors.